
Hair Growth Cycle Explained: Stages, Duration & Disruption in Malaysia

Interactive Hair Growth Cycle Guide Explore the biological phases of your hair and what triggers premature disruptions. 1. Anagen (Growth) 2. Catagen (Transition) 3. Telogen (Resting) 4. Disruption Anagen Phase (Active Growth) Cells in the root of the hair divide rapidly, adding to the hair shaft. Approximately 85% to 90% of scalp hair is in this phase, pushing hair upward to grow roughly 1 cm to 1.3 cm per month. Typical Duration: 2 to 7 years (Scalp) Catagen Phase (Regression Transition) A short transitional stage where the hair follicle detaches from the blood supply and shrinks to roughly one-sixth of its original size. Growth halts completely, converting the strand into a “club hair”. Typical Duration: 2 to 3 weeks Telogen Phase (Resting & Shedding) The hair follicle remains completely dormant while a new hair shaft begins to form underneath it. Eventually, old hairs are pushed out or shed naturally (around 50 to 100 hairs daily). Typical Duration: 2 to 4 months Cycle Disruption & Thinning Triggers like acute stress, postpartum changes, nutritional deficiencies, or Dihydrotestosterone (DHT) can prematurely force active follicles into early shedding phases (Telogen Effluvium) or miniaturize the roots. Common Catalyst: Stress, Hormones & Genetics Experiencing unusual hair shedding or thinning patterns in Malaysia? Get professional consultation. Chat via WhatsApp The hair growth cycle is a continuous physiological process consisting of four distinct stages: anagen (growth), catagen (transition), telogen (resting), and exogen (shedding). Each hair follicle operates independently, moving through these phases to ensure constant scalp coverage. Disruptions to this cycle can lead to noticeable thinning or premature hair loss. What Is the Hair Growth Cycle? Definition of Hair Growth Cycle Think of the hair growth cycle as the natural “lifecycle” of every single strand on your head. It is a biological loop where follicles produce hair, take a break, and eventually let the hair go to make room for a new one. Unlike some animals that shed seasonally, human hair cycles are asynchronous, meaning your hairs are all in different stages at once. In clinics across Kuala Lumpur, specialists use this cycle to diagnose whether your hair loss is temporary or a sign of permanent thinning that may need hair transplant Malaysia care. Why the Hair Growth Cycle Matters for Hair Health Understanding the cycle is the first step to realizing that some daily shedding is actually a sign of a healthy scalp. When your cycle is balanced, you maintain consistent “density,” even though you are losing hair every day. If the growth phase (anagen) shortens or the resting phase (telogen) lengthens, you will notice a visible loss of volume. Most professional treatments in Malaysia, such as , work by trying to “push” follicles back into the active growth stage. Stages of the Hair Growth Cycle Anagen Phase (Growth Phase) This is the “active” part of the cycle where cells in the root divide rapidly to create new hair. Approximately 85% to 90% of the hairs on your head are currently in this phase. The length of your hair is determined by how long your follicles stay in anagen; for most, this is several years. Catagen Phase (Transition Phase) This is a short, transitional “bridge” between growth and rest that lasts only about two to three weeks. During this time, the hair follicle shrinks and detaches from the dermal papilla (its blood supply). Only about 1% to 2% of your hair is in this stage at any given time. Telogen Phase (Resting Phase) The follicle remains dormant for about three months while a “club hair” (a hair that has stopped growing) stays in place. While the hair isn’t growing, the follicle is actually getting ready to start the whole process over again. Roughly 10% to 15% of your scalp hair is resting right now. Exogen Phase (Shedding Phase) This is the final “exit” where the old hair finally falls out, often during brushing or washing. The notes that exogen is distinct from the resting phase because it involves the active release of the hair shaft. New hair is usually already beginning to grow in the follicle as the old one leaves. How the Hair Growth Cycle Works Continuous Growth and Shedding Process Because each follicle acts on its own internal clock, you don’t lose all your hair at once. This staggered system ensures you always have a full head of hair while simultaneously renewing the “inventory.” If the system was synchronized, humans would go through periods of total baldness, similar to some mammals. Normal Cycle Balance in Healthy Hair In a healthy individual, the rate of new growth perfectly offsets the rate of shedding. A stable cycle means your hair maintains its “terminal length”—the maximum length it can grow before falling out naturally. Malaysian environmental factors, like high humidity, don’t change the cycle, but they can affect how the hair shaft feels and behaves. Duration of the Hair Growth Cycle How Long Each Phase Lasts Anagen: 2 to 7 years (this is why some people can grow hair to their waist while others can’t). Catagen: 10 to 20 days. Telogen: Approx. 100 days for scalp hair. These timings can vary slightly based on age, health, and ethnic background. Normal Hair Shedding Per Day It is scientifically normal to lose between 50 to 100 hairs per day. In some cases, especially if you have very long or thick hair, seeing up to 150 strands in the drain can still be considered within the normal range. The confirms that we often lose this much without even noticing it. Factors That Affect the Hair Growth Cycle Genetics and Hormonal Influence Your DNA determines your “base” anagen duration, which dictates your maximum hair length. Hormones like DHT (dihydrotestosterone) can cause follicles to spend less time in the growth phase, leading to “miniaturization.” Thyroid imbalances are a frequent cause of cycle disruption in both men and women. Stress and Lifestyle Factors Physical or emotional trauma can “shock” hairs out of the growth phase and into the resting phase prematurely. Lack of
Dihydrotestosterone (DHT): Functions, Hair Loss, and How to Manage It
Dihydrotestosterone (DHT) is a potent androgen sex hormone synthesized from testosterone through the 5-alpha reductase enzyme. While crucial for male physical development during puberty, elevated or highly sensitive DHT levels in adults are the primary biological driver behind male and female pattern baldness, stubborn adult acne, and prostate enlargement. What is Dihydrotestosterone (DHT)? Dihydrotestosterone, commonly abbreviated as DHT, belongs to the androgen family—a group of hormones responsible for producing male physical characteristics. Although often viewed as an unwanted hormone due to its link to hair thinning, it plays a vital role in early human biology, directing the development of male genitalia in the womb and driving secondary sexual characteristics like a deep voice and body hair during puberty. The Difference Between Testosterone and DHT While closely related, Testosterone and DHT function differently within the human endocrine system: Testosterone: The primary male sex hormone. It is highly active in the bloodstream and is responsible for regulating sex drive, spermatogenesis, bone density, and muscle mass building. Dihydrotestosterone (DHT): A metabolite of testosterone, converted locally within tissues by the 5-alpha reductase (5-AR) enzyme. DHT is significantly more potent than testosterone; it binds to androgen receptors in the skin, scalp, and prostate with up to five times greater affinity, causing a much stronger cellular response. Normal DHT Levels in Men and Women Hormone concentrations fluctuate based on age, gender, and overall health. Standard laboratory reference ranges generally look like this: Demographic Normal DHT Range (Serum) Key Biological Role Adult Men 10 to 85 ng/dL Prostate function, facial/body hair growth Adult Women 4 to 22 ng/dL Precursor for estrogen, maintaining tissue health How DHT Causes Hair Loss The most talked-about impact of DHT is its destructive relationship with the hair follicles on your scalp, leading to androgenic alopecia, which a hair transplant clinic can assess and treat. The Science Behind Male Pattern Baldness In men genetically predisposed to pattern baldness, hair follicles on the hairline, vertex, and crown possess a high concentration of androgen receptors. When DHT binds to these receptors, it triggers a progressive biological shutdown: Follicle Miniaturization: The physical size of the hair follicle shrinks, restricting its blood and nutrient supply. Anagen Phase Shortening: The active growth phase of the hair cycle drops from years down to months, while the resting phase expands. Vellus Hair Transition: With every consecutive cycle, the hair strand grows back thinner, shorter, and more brittle, transitioning from thick terminal hair into fine, invisible vellus hair until the follicle shuts down entirely. Does DHT Cause Female Pattern Hair Loss? Yes. While women produce far less dihydrotestosterone (DHT) than men, they can still experience Female Pattern Hair Loss (FPHL). This occurs when a woman has a genetic sensitivity to androgens or experiences a drop in protective hormones like estrogen (such as during menopause). In women, this hormone causes diffuse thinning across the entire top of the scalp and a widening of the hair parting line, though the frontal hairline usually remains intact. “Think of Dihydrotestosterone (DHT) like that one overzealous guest at a makan party who takes over the entire table and leaves no food for anyone else. In our bodies, too much DHT kicks our hair roots off the scalp, shrinking them until they can’t grow. By keeping this hormone in check, we pull back that unwanted guest, giving your hair follicles the space to thrive.” – Prof. Dato’ Dr. JasG, ABHRS-Certified Hair Transplant Doctor in Malaysia Symptoms of Hormonal Imbalance: High vs. Low DHT Imbalances in DHT levels can present noticeable physical symptoms across both genders. Signs of High DHT (Acne, Body Hair, and Prostate Enlargement) When your body produces an excess of DHT, or if your tissues are hypersensitive to it, you may experience: Severe Acne: DHT stimulates the sebaceous (oil) glands in your skin, leading to overproduction of sebum, clogged pores, and painful cystic acne along the jawline and back. Hirsutism: Paradoxically, while DHT shuts down hair on the scalp, it stimulates hair follicles on the body, leading to excess facial, chest, and back hair growth (especially noticeable in women with PCOS). Benign Prostatic Hyperplasia (BPH): In aging men, elevated localized DHT causes the cells of the prostate gland to multiply, resulting in an enlarged prostate that compresses the urethra and causes urinary difficulties. What Happens When DHT Levels Are Too Low? Low DHT is rarely an issue for adult women, but in men, abnormally low levels can lead to: Delayed or incomplete sexual development if it occurs during puberty. Reduced facial and body hair density. Increased risk of metabolic issues, though muscle mass usually remains unaffected since muscle tissue relies primarily on testosterone. How to Lower DHT Levels Safely Managing your DHT levels requires target-blocking the 5-alpha reductase enzyme to halt the conversion process. Clinical Medications and DHT Blockers Pharmaceutical treatments offer the most reliable, clinically proven method for reducing DHT activity: Finasteride: An oral medication that selectively blocks the Type II 5-AR enzyme, reducing serum DHT levels by roughly 70%. It is highly effective at stopping hair loss and shrinking an enlarged prostate. Dutasteride: A stronger dual-inhibitor that blocks both Type I and Type II enzymes, reducing circulating DHT by more than 90%. It is commonly prescribed for BPH and used off-label for severe hair thinning. Topical Anti-Androgens: Serums containing medications like minoxidil or prescription topical finasteride can treat the scalp locally, protecting hair follicles without lowering systemic DHT levels in the blood. Natural Remedies and Dietary Changes to Reduce DHT For a more holistic approach, certain botanical ingredients and lifestyle changes can help balance your hormones naturally: Saw Palmetto: A herbal extract that works similarly to finasteride, mildly inhibiting 5-AR to slow hair shedding. Pumpkin Seed Oil & Green Tea: Consuming pumpkin seed oil or drinking EGCG-rich green tea helps slow the hormonal conversion pathway. Lycopene-Rich Foods: Incorporating cooked tomatoes, carrots, and watermelon into your diet provides lycopene, an antioxidant that naturally regulates androgen activity. Testing and Diagnosis If you suspect your hair loss, acne, or urinary symptoms are tied to a
Ludwig Scale: Understanding Female Pattern Hair Loss Stages
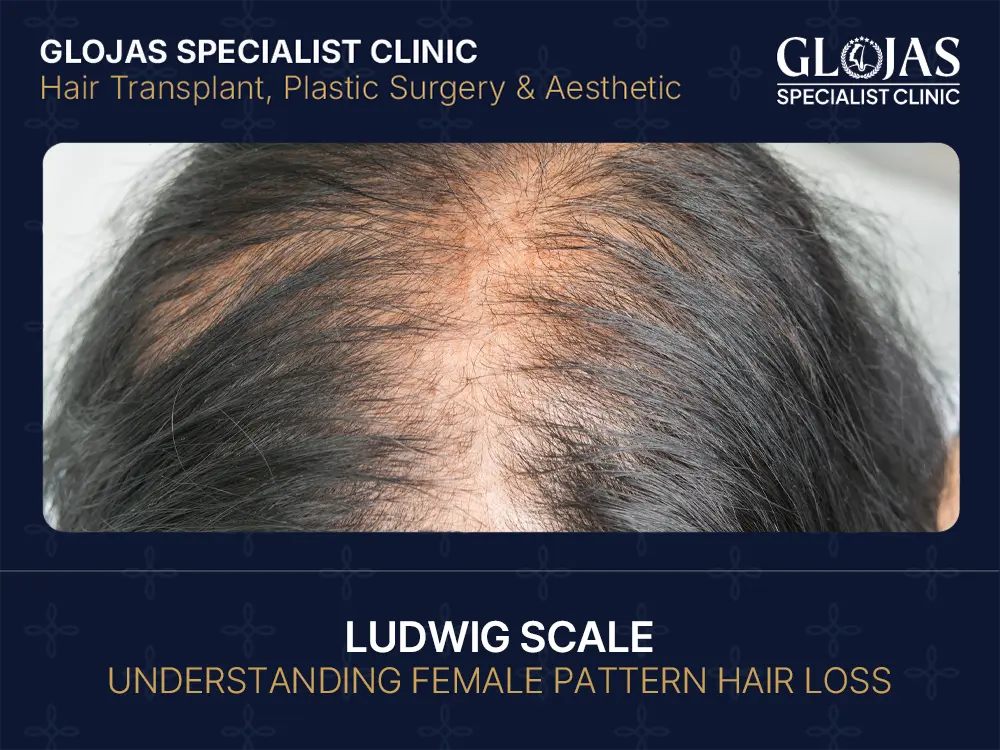
Interactive Ludwig Scale Stages Select a stage below to understand the progression of Female Pattern Hair Loss. Stage I Stage II Stage III Stage I: Mild Thinning Hair thinning begins perceptibly along the central parting. The hairline itself remains intact, but overall volume and density decrease noticeably at the crown. Stage II: Moderate Thinning Pronounced widening of the central part with a marked reduction in hair density. The scalp becomes significantly more visible across the top of the head. Stage III: Advanced Thinning Full-scale diffuse thinning across the crown, resulting in a sparse, see-through appearance where the scalp is prominently exposed. Consult Expert on WhatsApp Managing thinning hair can be an emotional journey, but the Ludwig Scale provides a scientific framework to navigate it. In Malaysia’s tropical climate—where humidity and sweat can make hair appear flatter—understanding these stages is vital for early detection. This guide offers an insightful analysis of how to recognize, diagnose, and treat female hair loss effectively. What Is the Ludwig Scale? Definition of Ludwig Scale The Ludwig Scale is a specialized clinical tool used by doctors to categorize the severity of Female Pattern Hair Loss (FPHL). Introduced in 1977, it remains the global standard for identifying diffuse thinning. Unlike male hair loss, which often follows a receding hairline, the Ludwig Scale tracks thinning that radiates from the center of the scalp. Why Ludwig Scale Is Used for Female Hair Loss This scale is essential because female hair loss is biologically distinct. Women rarely go completely bald; instead, their follicles shrink, leading to finer and shorter hairs (miniaturization). By using this scale, qualified aesthetic doctors in Malaysia can distinguish between temporary shedding (telogen effluvium) and chronic genetic thinning, ensuring a targeted treatment plan. Ludwig Scale Stages Ludwig Stage I: Mild Thinning Stage I represents the earliest sign of thinning, characterized by a slight widening of the central part line. Interestingly, many women miss this stage because the frontal hairline remains intact. Insight: If you notice your scalp becomes more visible under bright sunlight or when your hair is wet, you may be in this manageable early phase. Ludwig Stage II: Moderate Hair Loss At Stage II, thinning becomes significant. The part line widens noticeably, and there is a general decrease in volume. This is often the “tipping point” where women seek professional hair restoration. The scalp is easily seen, and styling becomes more difficult as the hair lacks the density to hold its shape. Ludwig Stage III: Advanced Diffuse Hair Loss Stage III is the most advanced level, where the hair on the crown is so sparse that the scalp is clearly visible. While the front hairline usually stays, the top of the head appears significantly bald. At this stage, non-surgical treatments focus more on stabilization rather than full regrowth, often requiring a combination of therapies. Causes of Ludwig Pattern Hair Loss Hormonal Changes The primary driver is Dihydrotestosterone (DHT). While women have lower levels of androgens than men, some are genetically more sensitive to them. Analysis: In Malaysia, conditions like Polycystic Ovary Syndrome (PCOS) can cause hormonal spikes that accelerate Ludwig-pattern thinning, making it a metabolic as well as an aesthetic concern. Genetic Factors Your DNA determines how your follicles react to age and hormones. If your female relatives experienced thinning, your follicles are likely programmed for a shorter growth phase. Understanding your family history allows for “preventative aesthetics,” where you start maintenance treatments before visible thinning even begins. Menopause-Related Hair Loss Menopause causes a sharp drop in estrogen, which previously protected your hair. This shift leaves androgens “unopposed,” often causing a rapid progression from Stage I to Stage II. In Malaysia’s aging population, hormone replacement therapy combined with scalp treatments is becoming a standard approach for restoring hair density. How Ludwig Scale Is Diagnosed Scalp Examination A doctor will perform a physical check, often using dermoscopy to look for follicle miniaturization. This high-magnification view reveals the ratio of thick “terminal” hairs to thin “vellus” hairs. This is the most reliable way to confirm an FPHL diagnosis and rule out other scalp conditions. Hair Density Assessment Clinicians use the “pull test” to see if hair is actively shedding. If fewer than three hairs come away during a gentle pull of 50 hairs, the issue is likely Ludwig pattern thinning rather than a temporary shedding event. This distinction is critical because shedding and thinning require entirely different medical protocols. Medical Consultation In Malaysia, an LCP-certified doctor will also check for iron deficiency, thyroid issues, and Vitamin D levels. Insight: Many Malaysian women suffer from low ferritin (stored iron), which mimics or worsens FPHL. A blood test ensures that you aren’t just treating the symptoms, but also any underlying systemic causes of hair loss. Treatment Based on Ludwig Scale Treatment for Ludwig Stage I At this stage, the goal is preservation. Topical Minoxidil (2% or 5%) is the gold standard for extending the hair’s growth cycle. When started early, many women see a 20–40% increase in hair density. Combining this with a nutrient-rich diet can often halt progression for years. Treatment for Ludwig Stage II Moderate thinning requires “biological boosting.” Platelet-Rich Plasma (PRP) or Exosome therapy are now the 2026 standards in Malaysia. These regenerative treatments use growth factors to “re-wake” dormant follicles. For many, this restores enough density to close the widening part line and improve self-confidence. Treatment for Ludwig Stage III For advanced loss, FUE hair transplant offer a permanent solution. Modern AI-driven robotic systems now ensure high graft survival rates. However, even after surgery, patients must continue medical therapy to protect the non-transplanted hair from the ongoing effects of the Ludwig progression. Results and Progression Hair Loss Progress Over Time FPHL is a slow, progressive condition. It doesn’t happen overnight; rather, hairs get slightly thinner with every cycle. Insight: Because the change is gradual, many women lose 50% of their hair density before they even notice. This “silent progression” is why regular scalp checks are important for women over 30. Treatment Response by Stage
Donor Area: Why It Matters for Hair Transplant Success in Malaysia
What Is the Donor Area? The donor area is the specific region of your scalp or body where healthy hair follicles are harvested for transplantation. These follicles are genetically programmed to resist balding, making them the “seeds” for your new growth. It acts as the finite engine for any successful hair restoration journey. Where the Donor Area Is Located Most commonly, the donor area is found at the occipital and temporal regions—the back and sides of the head. These areas are physiologically distinct because they lack the receptors for Dihydrotestosterone (DHT), the hormone primarily responsible for androgenetic alopecia, ensuring the transplanted hair lasts a lifetime. Why Donor Area Is Critical for Hair Transplant Success Think of the donor area as your “savings account.” Success depends on the quality and quantity of available grafts. If the donor site is handled poorly, you risk visible thinning or “moth-eaten” patches. Protecting this area ensures you have enough coverage for both current and future hair loss needs. Types of Donor Areas While the scalp is the primary source, modern science allows surgeons to look elsewhere. Depending on your needs, a surgeon might use a mix of locations to achieve natural density and texture. Scalp Donor Area (Safe Zone Explained) The “Safe Donor Zone” is the horseshoe-shaped area that remains even in advanced hair loss. According to the International Society of Hair Restoration Surgery (ISHRS), follicles here are naturally permanent. Using hairs from outside this zone increases the risk that transplanted hair will eventually fall out. Body Hair Donor Area (Beard, Chest Use Cases) When scalp hair is insufficient, surgeons utilize Body Hair Transplantation (BHT). Beard hair is the top choice due to its thick caliber and rapid growth cycles. Chest and back hair are also options, though they often have different textures and shorter growth phases compared to scalp hair. Donor Area in Hair Transplant Techniques The method of extraction significantly impacts how the donor site heals and how many follicles survive. FUE Donor Area Extraction In Follicular Unit Extraction (FUE), surgeons use a micro-punch (usually 0.7mm to 0.9mm) to harvest individual units. This creates tiny circular wounds that heal without a linear scar. It’s ideal for those who prefer short hairstyles and want a faster recovery for the donor region. FUT Strip Method and Donor Impact Follicular Unit Transplantation (FUT) involves removing a thin strip of skin. While it leaves a linear scar, it often yields a higher number of high-quality grafts in a single session. This method is highly efficient for patients requiring maximum coverage without thinning out the entire back of the head. DHI Technique and Graft Handling Direct Hair Implantation (DHI) focuses on minimizing the time follicles spend outside the body. While the extraction process is similar to FUE, the specialized tools allow for precise depth control, which helps preserve the integrity of the surrounding donor tissue and minimizes trauma to the scalp. Donor Area Density and Graft Capacity Managing your “hair budget” is a balancing act. You cannot take every hair; you must leave enough to maintain a natural, full appearance in the back. How Many Grafts Can Be Safely Extracted A healthy donor area typically contains 6,000 to 8,000 grafts in total. However, a surgeon usually extracts only 2,500 to 4,000 grafts in one session. Overstepping this limit risks permanent thinning. Standard density is often measured in follicular units per square centimeter ($FU/cm^2$). Donor Area Limitations and Planning If you have a “tight” scalp or low density, your options are limited. Surgeons use trichoscopy to measure your $FU/cm^2$ before surgery. Planning for potential future hair loss is vital so you don’t exhaust your supply too early in life. Feature FUE Donor Impact FUT Donor Impact Scarring Tiny white dots (diffuse) Single linear scar Healing Time 7–10 days 14–21 days Graft Quality High (if handled well) Superior (due to strip) Max Harvest Higher risk of thinning High yield, leaves density Donor Area Healing and Recovery Healing is a biological process that requires patience. While the front (recipient area) gets the glory, the back needs the most care during the first week. Healing Timeline After Extraction Days 1–3: Small scabs form; slight swelling and redness. Days 4–7: Itching begins as skin heals; scabs start to flake off. Week 2: Redness fades; hair begins to grow around the extraction sites. Month 1: The area usually looks completely normal to the naked eye. Scarring, Regrowth and Appearance With FUE, “scarring” refers to hypopigmented dots that are usually invisible unless you shave your head. With FUT, the scar can be hidden by hair as short as a grade 2 or 3. Proper post-operative wound care is essential to minimize scar widening or visibility. Factors Affecting Donor Area Quality Not all donor areas are created equal. Genetics, age, and lifestyle play huge roles in whether you are a “Grade A” candidate. Hair Density, Thickness and Elasticity High density (more hairs per $cm^2$) allows for more harvesting. Thickness (shaft diameter) provides better “visual coverage.” For FUT, scalp elasticity—how much the skin stretches—determines how wide a strip can be taken safely without causing tension in the closure. DHT Resistance and Long-Term Stability The “Safe Zone” must be truly resistant to DHT. If a patient has DUPA (Diffuse Unpatterned Alopecia), the donor area itself is thinning. In such cases, a transplant is usually not recommended because the moved hair will eventually fall out, just like the hair on top. Previous Transplants and Overharvesting Risk Every surgery leaves scar tissue (fibrosis). If you’ve had multiple procedures, the donor area becomes tougher and the blood supply may be slightly reduced. A skilled surgeon must navigate these “used” areas carefully to avoid “overharvesting,” which results in a transparent, patchy look. Donor Area Care After Hair Transplant Proper maintenance prevents infection and speeds up the return to normalcy. Your clinic will provide a specific protocol, but general rules apply to everyone. Post-Procedure Care Tips Keep the area clean by gently dabbing with sterile saline or a prescribed wash. Sleeping on
Should You Get A Second Hair Transplant? Why?
Choosing to undergo a second hair transplant is a common step for many Malaysians looking to achieve their hair restoration goals. Whether you’re looking to add density or correct a previous procedure, Malaysia offers world-class clinics and experienced surgeons. This guide explores everything you need to know about planning your secondary hair restoration journey. GLOJAS Specialist Clinic offers advanced hair transplant Malaysia services, providing FUE procedures, personalized consultations, and natural-looking results with experienced doctors, making it a trusted choice for effective hair restoration solutions. What Is a Second Hair Transplant? Definition and Purpose A second hair transplant, often called a revision hair transplant, is a follow-up surgical procedure designed to enhance the results of an initial session. Its primary purpose is to address remaining bald patches or thin areas. By strategically relocating healthy follicles, surgeons can create a fuller, more youthful appearance that matches your aesthetic expectations. Why Patients Need a Second Procedure Many patients require a second session because hair loss is often progressive. While the transplanted hair is permanent, your original hair may continue to thin over time. According to the International Society of Hair Restoration Surgery (ISHRS), nearly 30% of patients require more than one procedure to maintain their desired density as they age. Who Needs a Second Hair Transplant? Poor Results from First Transplant Unfortunately, some patients experience subpar outcomes due to outdated techniques or poor graft handling at lower-quality clinics. A second procedure can fix “pluggy” hairlines or unnatural growth patterns. Expert surgeons in Malaysia use corrective methods to camouflage old scars and redistribute hair for a much softer, more natural-looking frame for the face. Hair Loss Progression After First Procedure Androgenetic alopecia doesn’t always stop after one surgery. If you had a transplant in your 20s, you might lose more native hair by your 30s or 40s. A second session helps “fill the gaps” created by ongoing recession. This ensures your hair restoration journey stays consistent with your changing facial structure and natural aging process. Low Density or Uneven Coverage Sometimes, a single session isn’t enough to achieve high-volume density, especially for those with extensive thinning. A second pass allows the surgeon to place new grafts between existing ones without damaging the blood supply. This layering technique is essential for achieving “high-definition” results that look thick and full even under bright, direct overhead lighting. Is a Second Hair Transplant Possible for You? Donor Area Availability The success of a second procedure depends entirely on your remaining donor supply. Surgeons must ensure that extracting more grafts won’t leave the back of your head looking sparse. Professional clinics in Malaysia use digital scalp analysis to measure your follicular unit density, ensuring at least 20-25% of donor hair remains for a natural look. Hair Loss Stage Assessment Your surgeon will evaluate your current stage on the Norwood Scale to determine if a second procedure is viable. It is crucial that your hair loss has stabilized through medical management like Minoxidil or Finasteride. Operating on an unstable scalp can lead to “island” patches where the transplanted hair stays but the surrounding native hair disappears. Ideal Candidate Criteria The ideal candidate for a second transplant has a healthy scalp, realistic expectations, and sufficient donor hair. In Malaysia, the Malaysian Medical Council (MMC) guidelines emphasize patient safety and psychological readiness. You should also be in good general health, as conditions like uncontrolled diabetes can negatively impact the survival rate of the newly implanted hair grafts. Types of Second Hair Transplant Procedures FUE for Second Transplants Follicular Unit Extraction (FUE) is the most popular method for secondary procedures because it is minimally invasive and leaves no linear scar. Surgeons individually harvest follicles to fill specific thinning spots. This technique is perfect for patients who prefer short hairstyles, as the tiny “dot” scars are virtually invisible to the naked eye after healing. FUT in Revision Cases Follicular Unit Transplantation (FUT), or the strip method, is sometimes used if a patient has a very tight donor area or requires a large number of grafts. While it involves a linear scar, it can maximize the yield from the “safe donor zone.” Skilled surgeons can often excise the old scar from a previous FUT while performing the new one. Repair and Correction Techniques Revision surgery often requires specialized “stealth” techniques to fix mistakes from the past. This might include removing poorly placed, large grafts and “recycling” them into smaller, natural units. Surgeons may also use Scalp Micropigmentation (SMP) alongside the transplant to create the illusion of even greater density in areas where donor hair is becoming limited. Benefits of a Second Hair Transplant Improved Density and Coverage The most immediate benefit is a significant boost in hair thickness. By adding 1,500 to 2,500 additional grafts, surgeons can effectively double the visual density in key areas like the crown or frontal forelock. This creates a much more robust look that allows for more versatile styling options and increased personal confidence in social settings. Correction of Hairline Design A second chance allows you to refine a hairline that may have been placed too high or too low during the first round. Trends change, and your face shape evolves; a revision lets you “modernize” your look. Refined hairline design principles ensure that the transition from forehead to hair is soft, irregular, and indistinguishable from nature. More Natural Results Advancements in technology mean that a second transplant often looks better than the first. Modern tools allow for smaller incisions and more precise angulation of the hair. This results in a “seamless” blend where the new hair follows the exact direction of your existing growth, eliminating the “doll-hair” look often associated with older, less sophisticated transplant methods. Risks of a Second Hair Transplant Limited Donor Hair Every person has a finite amount of donor hair. Over-harvesting the back of the head can lead to a “moth-eaten” or patchy appearance. It is a delicate balancing act; taking too much can compromise the aesthetic of the donor site. Ethical surgeons will